The biomechanical validation of a cervical plate poses a significant challenge for manufacturers of medical devices intended for spinal surgery. Before proceeding to market, it is necessary to demonstrate that the system—consisting of the plate, screws, vertebrae, and bone graft—exhibits adequate mechanical performance under flexion, extension, torsion, and compression loads.
Cadaver studies can provide relevant information, but they also have limitations that make it difficult to objectively compare different study designs: limited availability of specimens, anatomical variability, differences in bone quality, and difficulties in exactly replicating the same experimental conditions.
To address this problem, the Biomechanics Institute of Valencia developed a methodology that combined mechanical testing with finite element modeling. The goal was to evaluate the behavior of two types of anterior cervical plates without relying exclusively on in vitro testing using cadaveric specimens.
This case study demonstrates how the integration of physical experimentation, computational simulation, and biomechanical knowledge can help reduce uncertainties, compare designs, and provide useful information for the development of implantable medical devices.
The challenge: evaluating cervical images with comparable and reproducible results
Cervical arthrodesis is a surgical procedure designed to fuse two or more vertebrae. After decompressing the nerve structures, a bone graft is placed between the vertebrae, and an anterior cervical plate secured with screws is used to provide stability to the entire structure.
From a design perspective, there are two main families of boards:
Static cervical plates
In these systems, the movement of the screws relative to the plate is restricted. Their primary function is to provide a rigid fixation between the vertebral segments.
Dynamic cervical plates
They allow for some movement of the screws relative to the plate. This movement is intended to facilitate the transfer of load to the bone graft and maintain contact between the graft and the vertebrae during the fusion process.
To compare these two concepts, it is not enough to simply determine which one can support a greater load. It is necessary to examine:
- how the load is distributed between the bone and the graft;
- what stresses occur in the implant;
- how the adjacent vertebrae respond;
- how behavior changes when the graft’s condition is altered;
- and what happens under different physiological stress conditions.
The problem is that the inherent variability in cadaver samples can mask differences attributable to the design of the medical device.
Major Limitations of Cadaver Studies
| Limitation | Consequences for the manufacturer |
|---|---|
| Limited availability of samples | Difficulty in planning large-scale trial campaigns |
| Anatomical Variability and Bone Quality Variability | Results that are less comparable across samples |
| Differences Between Assemblies | Lower experimental repeatability |
| Cost and Logistical Complexity | Increased investment during development |
| Limited number of scenarios | Difficulty in studying multiple designs, sizes, or pathologies |
| Restrictions on Retaking the Test | Reduced ability to test design hypotheses |
These limitations do not preclude the use of cadaveric samples, but they do justify the search for complementary methodologies that are more controllable and reproducible.
The IBV Solution: Combining Mechanical Testing and Finite Element Analysis
The IBV proposed a two-tiered strategy.
On the one hand, he conducted mechanical tests on simplified physical assemblies capable of reproducing the behavior of the assembly in a controlled manner. On the other hand, he created finite-element models of the spine-implant system, which he used to analyze variables that are difficult to measure directly through experimentation.
The methodology followed a step-by-step process:
- Experimental characterization of cervical plates.
- Development of computational models.
- Validation of the models using experimental results and the literature.
- Integration of the plate, screws, graft, and cervical spine into a single model.
- Application of loads and boundary conditions.
- Comparison of Static and Dynamic Plates.
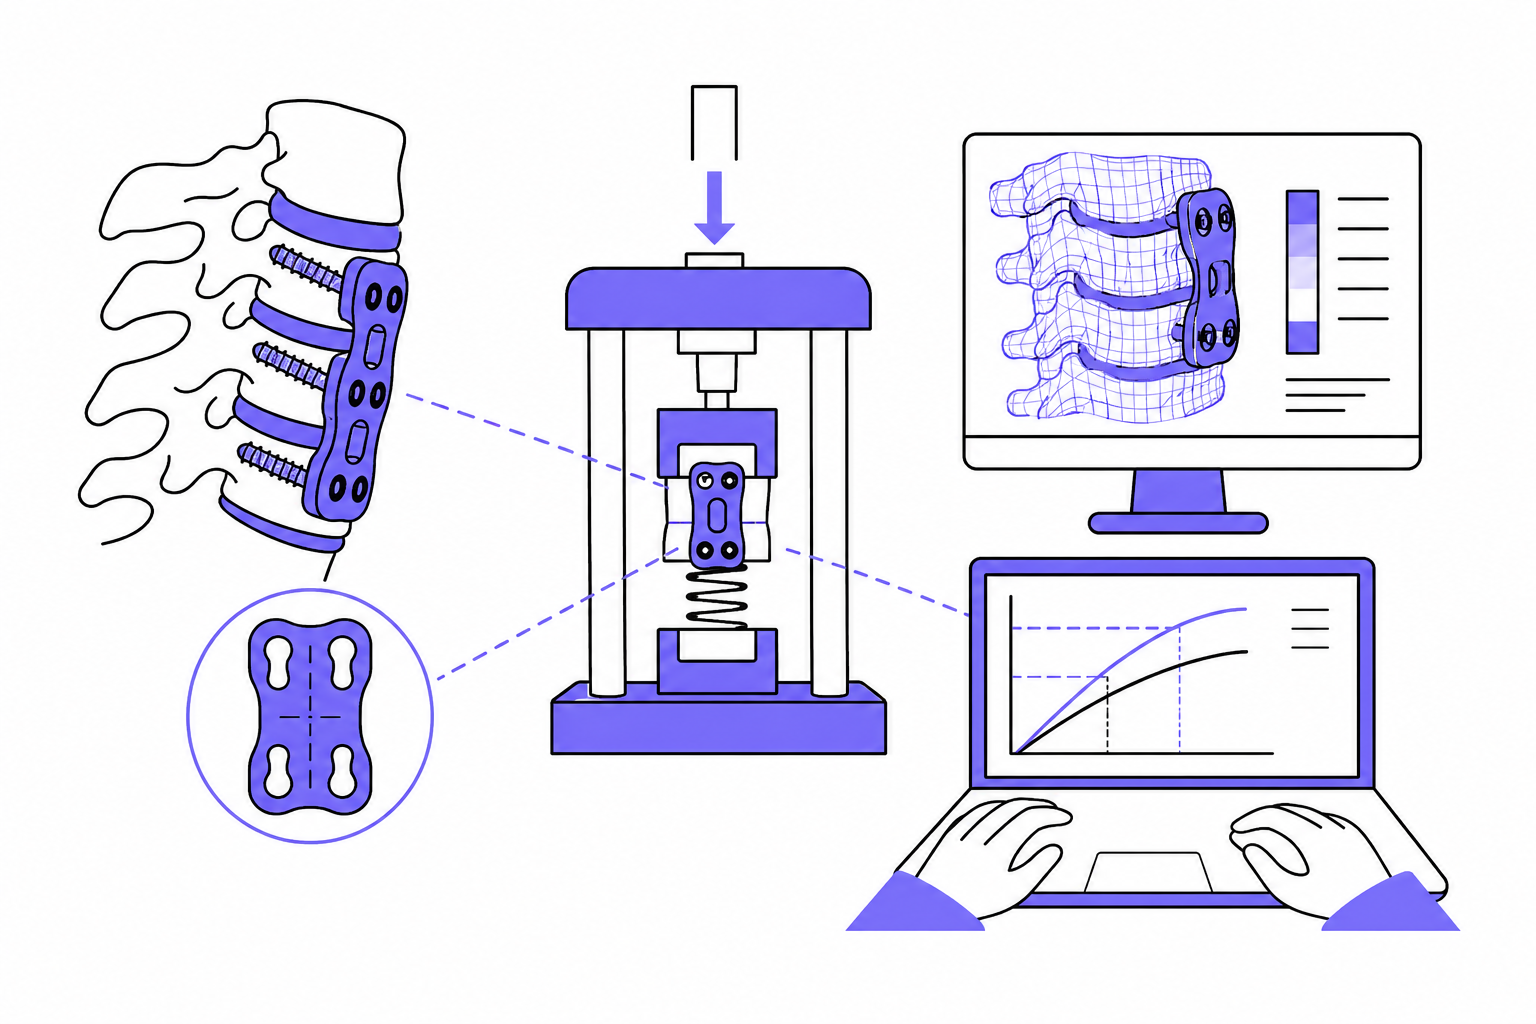
The diagram on the second page of the document clearly illustrates this connection between mechanical testing, the literature, model validation, and the final biomechanical evaluation.
Mechanical testing with a controlled setup
For the tests, the vertebral bodies were simulated using polyethylene blocks, while the bone graft was represented by a spring with a known stiffness.
The setup was based on ISO 12189:2008, which pertains to the mechanical testing of anteriorly supported spinal implant systems. This configuration allowed for the application of compressive loads and the acquisition of force-displacement curves with low experimental variability.
What information did the trials provide?
The force-displacement curves made it possible to:
- assess the stiffness of the plates;
- identify the displacement of the screws on the dynamic plates;
- to analyze the response to a simulated graft shortening;
- and objectively compare the behavior of static and dynamic plates.
In the case of the dynamic plate, the screws were observed to shift until the upper block came into contact with the element simulating the graft. In the static plate, this coupling mechanism could not occur.
This result made it possible to experimentally demonstrate a functional difference between the two concepts of plaque.
Finite element models of the rachis-implant assembly
The second part of the methodology involved developing a finite-element model of the cervical spine that would represent:
- spinal geometry;
- bone materials;
- the ligaments;
- the intervertebral discs;
- the cervical plate;
- the anchor screws;
- and bone grafting.
The model was also intended to allow for the simulation of clinical abnormalities, such as the removal of an intervertebral disc or a vertebral body.
Once the spine-implant assembly had been integrated, flexion, extension, and torsion loads were applied to study the biomechanical response of the two plate designs.
What are the advantages of simulation over mechanical testing?
| Mechanical Testing | Finite Element Model |
|---|---|
| Measure the overall response of the assembly | Shows the internal stress distribution |
| Provides force-displacement curves | It allows you to study the plate, screws, graft, and vertebrae separately |
| Validate the experimental results | It allows you to simulate multiple clinical scenarios |
| Compare physical prototypes | Compare designs before building new prototypes |
| Identifies stiffness and displacements | Locates stress concentrations |
| It requires the manufacture and assembly of samples | Facilitates the virtual analysis of dimensions, geometries, and load conditions |
The main advantage is not to indiscriminately replace experimentation, but rather to use both approaches in a complementary manner. Experiments serve to validate the model, and the model expands upon the information obtained experimentally.
Results: Biomechanical Differences Between Static and Dynamic Plates
The methodology made it possible to compare how the load was distributed across both types of plates.
In the static plate models, a greater proportion of the load was transmitted through the plate. This resulted in higher stresses on the implant and a lower load on the bone graft.
In dynamic plates, the movement allowed by the screws promoted contact and load transfer to the graft. From a biomechanical perspective, this information was relevant because the load borne by the graft can influence the mechanical environment of the spinal fusion.
The analysis was not limited to determining which plate was stiffer. It made it possible to study the following simultaneously:
- the percentage of the load transmitted by the graft;
- the percentage supported by the plate;
- stresses in the medical device;
- and the stresses generated in the adjacent vertebrae.
Value for the Development of Spinal Medical Devices
This case study demonstrates that combining mechanical testing and simulation can yield significant benefits during the design, verification, and optimization phases.
Reducing Experimental Variability
Polyethylene blocks and elements of known stiffness allow for the creation of comparable assemblies. Thus, the differences observed are more directly related to the plate design.
Objective Comparison of Alternatives
The methodology allows for the comparison of static and dynamic plates, but it can also be adapted to the study of different geometries, sizes, materials, or fastening systems.
Early Detection of Critical Points
Simulation helps identify stress concentrations before manufacturing new iterations, reducing the risk of discovering problems in later stages.
Evaluation of Scenarios That Are Difficult to Reproduce
The models allow users to modify the condition of the graft, the vertebral geometry, or the loading conditions without having to rely on a new physical specimen for each scenario.
Generation of more comprehensive technical evidence
The combination of experimental and numerical data provides a more comprehensive biomechanical interpretation than a single result for maximum load or stiffness.
How This Methodology Improves R&D Decision-Making
For a manufacturer, the question isn’t just whether a circuit board passes a test. They also need to know why it behaves a certain way and what changes could improve it.
A combined strategy can help answer questions such as:
- Which part of the implant experiences the most stress?
- How does screw design affect load distribution?
- What happens when the graft loses height?
- How does the response change under bending, extension, or torsion?
- What are the differences between sizes?
- Is it possible to reduce material without compromising performance?
- Which configuration represents the worst-case scenario?
Answering these questions before finalizing the design can reduce the number of iterations and facilitate a more well-founded validation strategy.
A case study of applied experience that reinforces the IBV’s expertise
This project is not merely a theoretical concept. It is a methodology developed and applied by a multidisciplinary team composed of specialists from the IBV, CIBER-BBN, and the clinical departments of Neurosurgery and Orthopedic and Traumatology Surgery.
The collaboration between engineering, biomechanics, and clinical practice made it possible to develop a model that accurately represented the real-world problem and to analyze variables relevant to the implant’s performance. The project also received plates donated by AESCULAP and the B. Braun Group, as well as funding from Fundación MAPFRE.
This combination of technical expertise, clinical collaboration, and experimental application provides direct evidence of experience in the biomechanical evaluation of implantable medical devices.
Current Application of This Experience at Med-Lab IBV
The experience gained from projects like this one underpins Med-Lab IBV’s current approach to the evaluation of medical devices:
- definition of testing strategies;
- design of biomechanical setups;
- mechanical characterization;
- finite element simulation;
- analysis of critical cases;
- technical interpretation of results;
- and support for manufacturers during product validation.
For projects related to the spine, osteosynthesis, or other surgical implants, the key differentiator lies in integrating test execution with a deep understanding of biomechanics.
You can learn more about IBV’s capabilities in spinal implant testing and discuss the specific requirements for your medical device with the technical team.
Improve validation to reduce development risks
The evaluation of a cervical plate does not have to rely exclusively on tests using cadaveric specimens. The methodology developed by the IBV demonstrates that it is possible to combine reproducible mechanical tests with finite element models to obtain objective information on the stiffness, load distribution, and stresses of the spine-implant assembly.
The result is a strategy capable of:
- reduce variability;
- compare designs;
- analyze clinical scenarios;
- identify critical points;
- and improve decision-making prior to final validation.
For manufacturers, this approach allows them to turn testing into a development tool, rather than just a verification step at the end of the project.